Helping Clients Avoid Costly Medicare Mistakes: A 2026 Guide for Financial Advisors
October 12, 2026
Key Takeaways
- Medicare doesn't cover everything. Fidelity estimates that a single person retiring at 65 in 2026 will spend an average of $185,500 on health care in retirement, not including long-term care. Yet 54% of pre-retirees mistakenly expect Medicare to cover all of their health costs.
- Enrollment timing mistakes can be permanent. Missing the Initial Enrollment Period, or the eight-month Special Enrollment Period after job-based coverage ends, can trigger late penalties that last as long as the client has coverage. Open Enrollment (October 15 to December 7 each year) is the yearly chance to review and change plans.
- The right plan depends on how and where clients get care. Frequent travelers often lean toward Original Medicare, clients with complex health needs may add Medigap, and clients who stay local may prefer having medical and drug coverage in a single Medicare Advantage plan.
- As IRMAA surcharges are based on a two-year MAGI lookback, Roth conversions and any other income impacting moves can result in a higher Part B and Part D premium. RightCapital projects these costs and can model Roth conversions that stop at a chosen IRMAA tier or before triggering IRMAA.
Medicare covers a lot, but it doesn't cover everything. Fidelity Investments' 2026 Retiree Health Care Cost Estimate puts the average lifetime health care bill for one person who retires at 65 this year at $185,500. That figure rose 7.5% over last year's estimate, and it leaves out long-term care entirely. Fidelity bases the number on Original Medicare with Part D coverage, and nearly half of it (45%) is just Part B and Part D premiums.
Many people don't expect costs like these. In Fidelity's research, more than half of pre-retirees (54%) mistakenly assumed that Medicare, even with Part D and Medigap, would pay for all of their health costs. As Steve Betts, head of Fidelity Health, put it, "Medicare is a critical part of retirement health coverage, but it does not eliminate every health care expense."
That gap is where financial advisors add value. Clients often turn to their advisors during Medicare enrollment because there's a lot to weigh. To avoid lifelong late enrollment penalties, clients need to sign up at the right time, which depends on their age, whether they're collecting Social Security, and any existing coverage.
If any of your clients are looking to adjust their Medicare coverage, now is the time. Medicare's Open Enrollment Period runs from October 15 to December 7 every year. During this window, beneficiaries can switch between Original Medicare and Medicare Advantage, change Medicare Advantage plans, and join, drop, or switch Part D drug plans. Changes take effect January 1 of the following year.
This guide covers the most common Medicare mistakes, what each part of Medicare covers and costs in 2026, how to help clients choose coverage, how income related monthly adjustment amounts (IRMAA) works, when to enroll, and how RightCapital's Health Care module supports Medicare planning.
What are the most common Medicare mistakes clients make?
The most expensive Medicare mistakes usually involve timing and income. Based on rules published on Medicare.gov and Fidelity's research, watch for these seven:
- Missing the Initial Enrollment Period. Clients who don't sign up for Part B when they're first eligible (and who don't qualify for a Special Enrollment Period) may pay an extra 10% for each full year they could have enrolled, typically for as long as they have Part B.
- Going 63 days or more without drug coverage. For those not receiving Extra Help and after the Initial Enrollment Period, a gap of 63 days or more without Part D or other creditable drug coverage can trigger a permanent Part D penalty if they sign up for Part D at any point.
- Missing the eight-month Special Enrollment Period after leaving a job. The window starts when the client stops working or loses their employer coverage, whichever comes first. COBRA doesn't count as employer coverage here, so the clock keeps running even if the client signs up for COBRA. Waiting for COBRA to end can mean a gap in coverage and a lifetime Part B penalty.
- Letting the Medigap Open Enrollment Period pass. Once this one-time, six-month window closes, getting a policy can become harder or cost more.
- Assuming Medicare covers everything. Original Medicare has no yearly out-of-pocket limit for Part A or Part B, and Fidelity's $185,500 estimate doesn't include long-term care (ranging from ~26,000 a year for adult day care to ~$128,000 a year for a private nursing room home in 2026).
- Overlooking IRMAA when planning retirement income sources. Roth conversions and other moves that raises modified adjusted gross income (MAGI) can increase Part B and Part D premiums two years later.
- Skipping the annual Open Enrollment review. Medicare Advantage and Part D plan costs can change each year, so the plan that fit last year may not fit next year.
What does Medicare cover and what does it cost in 2026?

Cost | 2026 Amount |
|---|---|
Part A premium | $0 for most people; $311 or $565/month if purchased (based on client or co-client’s previous payments into Medicare) |
Part A deductible | $1,736 per benefit period |
Part B standard premium | $202.90/month |
Part B deductible | $283/year |
Part B premium with IRMAA | $284.10 to $689.90/month |
IRMAA income thresholds (based on 2024 MAGI) | Above $109,000 (individual) or $218,000 (joint) |
Part D maximum deductible | $615 ($700 in 2027) |
Part D out-of-pocket cap before catastrophic coverage kicks in | $2,100 ($2,400 in 2027) |
Part D IRMAA | $14.50 to $91/month on top of the plan premium |
Insulin (Part B and Part D) | No more than $35 for a one-month supply |
Sources: Medicare.gov; CMS for Part B IRMAA premium amounts.
Medicare Part A: hospital insurance
Most people pay no monthly premium for Part A. They qualify through Medicare taxes that they or their spouse paid during their working years, usually for a decade or more. Clients without premium-free Part A may be able to buy it for $311 or $565 per month, depending on how long they or their spouse worked and paid into Medicare, but they also have to enroll in Part B.
Part A mainly covers inpatient hospital stays when the patient is formally admitted with a doctor's order. Hospital costs are tracked in benefit periods. Each one begins on the day of inpatient admission and closes after the client has gone two straight months (60 consecutive days) without inpatient hospital or skilled nursing care. A new benefit period means a new deductible, and there's no cap on how many benefit periods a client can have in a year.
Inpatient hospital stay (per benefit period) | What the client pays in 2026 |
|---|---|
Deductible | $1,736 |
Days 1–60 | $0 per day after the deductible |
Days 61–90 | $434 per day |
Days 91–150 (lifetime reserve days) | $868 per day |
After day 150 | All costs |
Under these numbers, a 90-day hospital stay could cost a client $14,756 ($1,736 deductible plus 30 days at $434). Every person gets 60 lifetime reserve days in total, and once they're used, they're gone.
Part A also covers other kinds of care:
- Skilled nursing facility care: This coverage generally requires an inpatient hospital stay of at least three days in a row first, and the client usually needs to enter the facility within about 30 days of leaving the hospital. Days 1–20 cost $0 once the Part A deductible is met, days 21–100 cost $217 per day, and from day 101 on, the client pays all costs.
- Home health care: Clients pay nothing for certain covered home health services. For durable medical equipment such as a walker, wheelchair, or hospital bed, they owe 20% of what Medicare approves. Medicare doesn't pay for homemaker services, such as shopping and cleaning, that aren't part of the client's care plan.
- Hospice care: Clients pay nothing for covered hospice care, which is end-of-life care for terminally ill patients. Once hospice begins, Medicare no longer pays for treatment meant to cure the terminal illness. It also doesn't cover room and board for hospice care at home or in a nursing home, unless the hospice team arranges short-term inpatient or respite care. At home, pain and symptom-control prescriptions can carry a copay of as much as $5 each. Inpatient respite care costs 5% of what Medicare approves.
Original Medicare has no yearly out-of-pocket maximum for Part A or Part B unless the client has supplemental coverage, such as a Medigap policy, or joins a Medicare Advantage plan.
Medicare Part B: medical insurance
Part B pays for care from doctors and other providers, including outpatient services, home health care, ambulance services, durable medical equipment, oxygen equipment, and many preventive services such as screenings and vaccines. In 2026:
- Standard premium: $202.90 per month, or more for higher-income beneficiaries
- Annual deductible: $283
- Coinsurance: typically 20% of the Medicare-approved cost once the deductible is met, if the provider accepts assignment
Higher earners pay more for Part B through IRMAA, which is covered in detail below.
Medicare Part C: Medicare Advantage
Medicare Advantage plans come from private insurers that Medicare has approved. Instead of getting Part A and Part B benefits through Original Medicare, members get them through the Medicare Advantage plan, which usually bundles in Part D drug coverage too. According to Medicare.gov, many plans also add benefits Original Medicare doesn't cover, such as vision, hearing, and dental, making Medicare Advantage a potential all-in-one solution for some clients.
Some things for clients to keep in mind:
- Premiums, deductibles, copays, and coinsurance vary by plan, and enrollees must keep paying their Part B premium.
- Every plan has a yearly out-of-pocket limit. After a member hits that limit, the plan covers 100% of covered care through December 31.
- Members must live in the plan's service area, and they're more closely tied to local, in-network doctors. That can be a problem for clients who travel often or split the year between states.
Medicare Part D: prescription drug coverage
Part D is sold by private, Medicare-approved plans, so both the monthly premium and what clients pay at the pharmacy (deductibles, copays, and coinsurance) vary by plan.
- Deductible: No plan can have a deductible higher than $615 in 2026 ($700 in 2027), and some plans have no deductible.
- Out-of-pocket cap: After a client has paid $2,100 in 2026 ($2,400 in 2027) toward covered drugs, catastrophic coverage kicks in. From that point until the calendar year ends, covered Part D drugs cost them nothing.
- IRMAA: Higher earners pay an extra $14.50 to $91 per month on top of their plan premium in 2026, using the same income thresholds as Part B.
Recent changes to Medicare prescription drug costs
Several recent changes affect what Medicare beneficiaries pay for prescription drugs:
- Insulin is capped at $35 per month. Under both Part B and Part D, each covered insulin product costs $35 or less for a month's supply, with no deductible.
- There's now a yearly limit on Part D spending. It's $2,100 in 2026 and rises to $2,400 in 2027.
- Medicare is negotiating drug prices. Medicare can now negotiate what it pays for some high-cost brand-name drugs that lack competition. The first round of 10 negotiated Part D prices started on January 1, 2026, and a second round covering 15 more drugs starts January 1, 2027.
Medigap (Medicare Supplement Insurance)
Clients with Original Medicare can add a Medigap policy from a private insurer to pick up part of their share of costs, such as deductibles and coinsurance. Medigap is standardized, so a lettered plan (most states use A–D, F, G, and K–N) includes identical core benefits regardless of the insurer. The only thing that varies between insurers for the same letter is the price.
Timing matters. Clients get a one-time, six-month Medigap Open Enrollment Period that starts the first month they have Part B and are 65 or older. During that window, insurers can't turn a client down because of pre-existing health conditions. Once it closes, buying a policy can get harder or more expensive.
Medigap is sold only to people in Original Medicare, so clients in Medicare Advantage can't add it.
How should clients choose between Original Medicare, Medigap, and Medicare Advantage?
The best Medicare option depends on how much coverage clients need, where they get care, how often they need it, and how much cost uncertainty they can tolerate. A few patterns come up often:
Client profile | Option to consider | Why |
|---|---|---|
Travels often or spends winters in another state | Original Medicare, with or without Medigap | Clients can see any doctor or hospital that accepts Medicare. Medicare Advantage plans may require in-network doctors. |
Sees doctors often or has complex health needs | Original Medicare + Medigap | Premiums are higher, but out-of-pocket costs are more predictable and it covers more than original Medicare alone, which helps with ongoing medical expenses. |
Plans to stay local and wants one plan | Medicare Advantage with drug coverage | Medical and drug coverage come through a single plan with a yearly out-of-pocket limit. |
RightCapital's Health Care module uses these same factors to flag which options fit each client (see below).
How does retirement income affect Medicare premiums (IRMAA)?
IRMAA (income-related monthly adjustment amount) is an extra charge added to Medicare Part B and Part D premiums for higher-income beneficiaries. It's based on modified adjusted gross income (MAGI) from two years earlier, so 2026 premiums are based on 2024 tax returns.
For 2026, IRMAA starts when 2024’s MAGI is above $109,000 for individual filers or $218,000 for joint filers. According to Centers for Medicare & Medicaid Services (CMS), in 2026, total Part B premiums for these higher earners run from $284.10 to $689.90 per month, and Part D IRMAA adds $14.50 to $91 per month on top of the plan premium.
The two-year lookback means that retirement income decisions today can change Medicare costs two years from now. Strategies that add taxable income, such as Roth conversions, can raise MAGI enough to push a client into a higher IRMAA tier. If it’s not considered in those conversations, it can be quite the shock for clients to find they paid not only a higher tax bill upfront, but also will keep paying for it two years in the future.
RightCapital helps advisors see these trade-offs. In the Tax Strategies module, you can set a Roth conversion target based on Medicare premium (IRMAA) brackets. Then use the "Fill up the tax bracket" slider to convert as much as possible each year without going over the IRMAA threshold you choose or without triggering IRMAA. The Calibration tab charts the household's projected MAGI against each IRMAA threshold. The Details tab shows MAGI, IRMAA thresholds, and Medicare premiums year by year, so clients can see what a strategy means for both their taxes and their health care costs.
When should clients enroll in Medicare?
Most clients should enroll during their seven-month Initial Enrollment Period, which starts three months before the month they turn 65 and ends three months after it. Signing up at the wrong time can lead to coverage gaps and late enrollment penalties that last for life.
Enrollment period | When it happens | What clients can do |
|---|---|---|
Initial Enrollment Period | 7 months around the 65th birthday (3 months before the birthday month, the birthday month, and 3 months after the birthday month) | Sign up for Part A, Part B, and a Medicare Advantage or Part D plan |
Special Enrollment Period (job-based coverage ending) | 8 months after employment or job-based coverage ends, whichever comes first | Sign up for Part B without a late penalty |
Medigap (Protected) Open Enrollment Period | 6 months starting the first month of Part B at age 65+ | Buy any Medigap policy without being denied for pre-existing conditions |
Open Enrollment Period | October 15 – December 7 each year | Switch between Original Medicare and Medicare Advantage, change plans, or join, drop, or switch Part D (effective January 1 the following year) |
Medicare Advantage Open Enrollment Period | January 1 – March 31 each year, or the first 3 months of Medicare | Switch Medicare Advantage plans or return to Original Medicare (Medicare Advantage members only) |
A few details to keep in mind:
- Automatic enrollment: Clients whose Social Security benefits begin four or more months before their 65th birthday are enrolled in Parts A and B automatically. Clients who aren't getting Social Security yet need to sign up themselves.
- Still working at 65: Clients (or spouses) covered by a group health plan through current employment may be able to delay Part B. The eight-month Special Enrollment Period starts when they stop working, even if they choose COBRA.
- Part D: To avoid the Part D penalty, clients shouldn't go 63 days or more without Part D or other creditable drug coverage after their Initial Enrollment Period ends.
What are the Medicare late enrollment penalties?
Coverage | Late enrollment penalty |
|---|---|
Part A (if purchased) | Premium may rise 10%, paid for twice the number of years the client could have enrolled but didn't |
Part B | An extra 10% for each full 12-month period the client could have enrolled but didn't, typically paid for as long as they have Part B |
Part D | An extra 1% of the national base beneficiary premium ($38.99 in 2026) for each month without coverage, paid for as long as they have Part D |
With RightCapital’s RightIntel (included with Premium and Platinum subscriptions), you can see when each client reaches Medicare filing age in the Key Events table. The table shows the month and calendar year each milestone happens, so you can spot upcoming Medicare conversations. You can also turn on key event notifications to be alerted when clients reach Medicare filing age.
How does RightCapital help advisors with Medicare planning?
RightCapital's Health Care module (formerly the Medicare module) brings retirement health care cost projections, Medicare option comparisons, and enrollment guidance together in one place. You'll find it under Retirement > Health Care in any client plan. The module has three sub-tabs.
“Preferences” tab
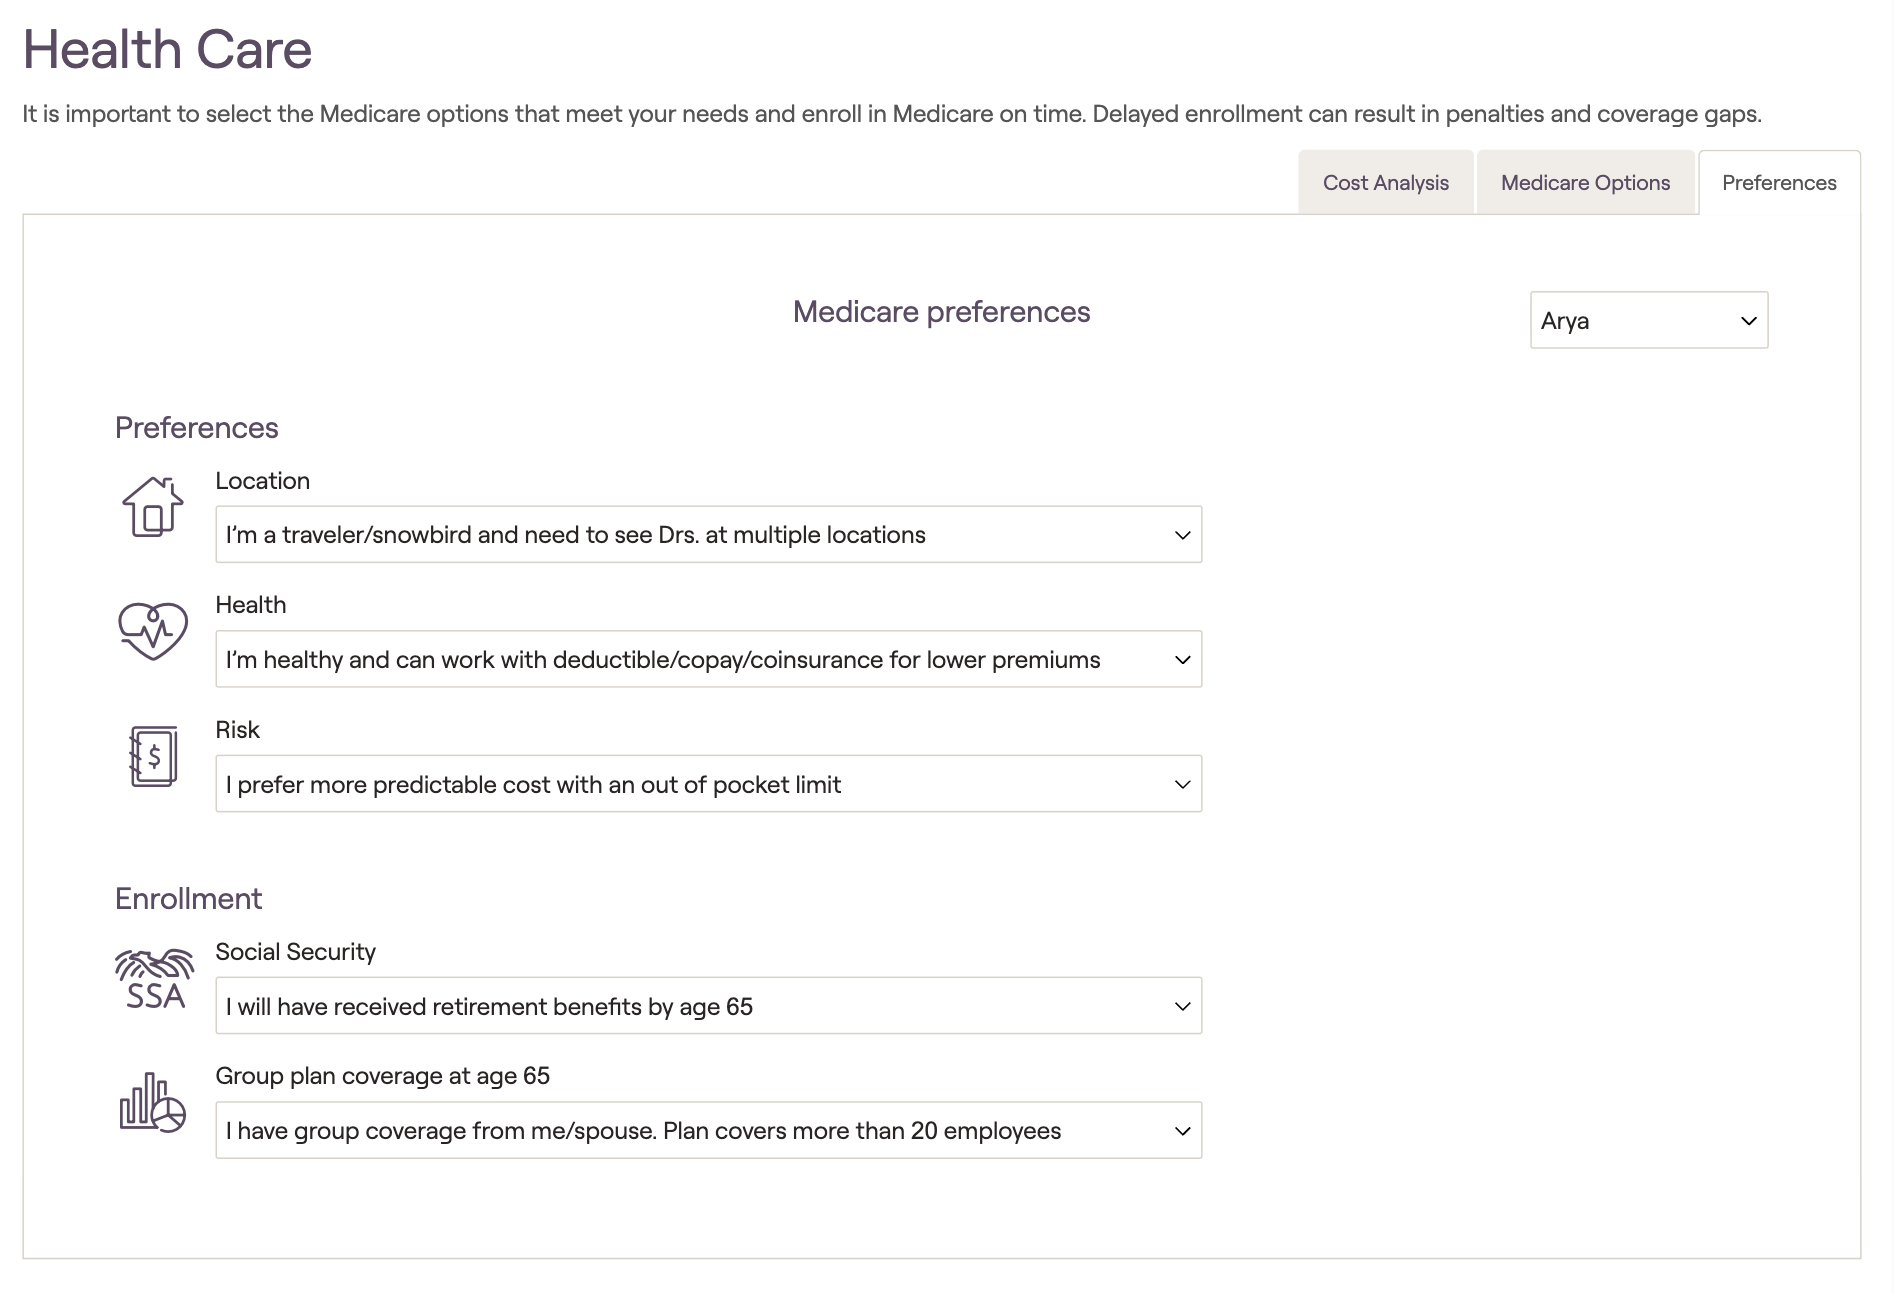
RightCapital uses these answers to show which Medicare options fit the client and if they have any clear Special Enrollment Periods to note.
For example, if a client says they're a traveler or snowbird who needs to see doctors in different places, Original Medicare options get a checkmark. Medicare Advantage gets a red "X" because those plans tie members more closely to local, in-network doctors.
“Medicare Options” tab
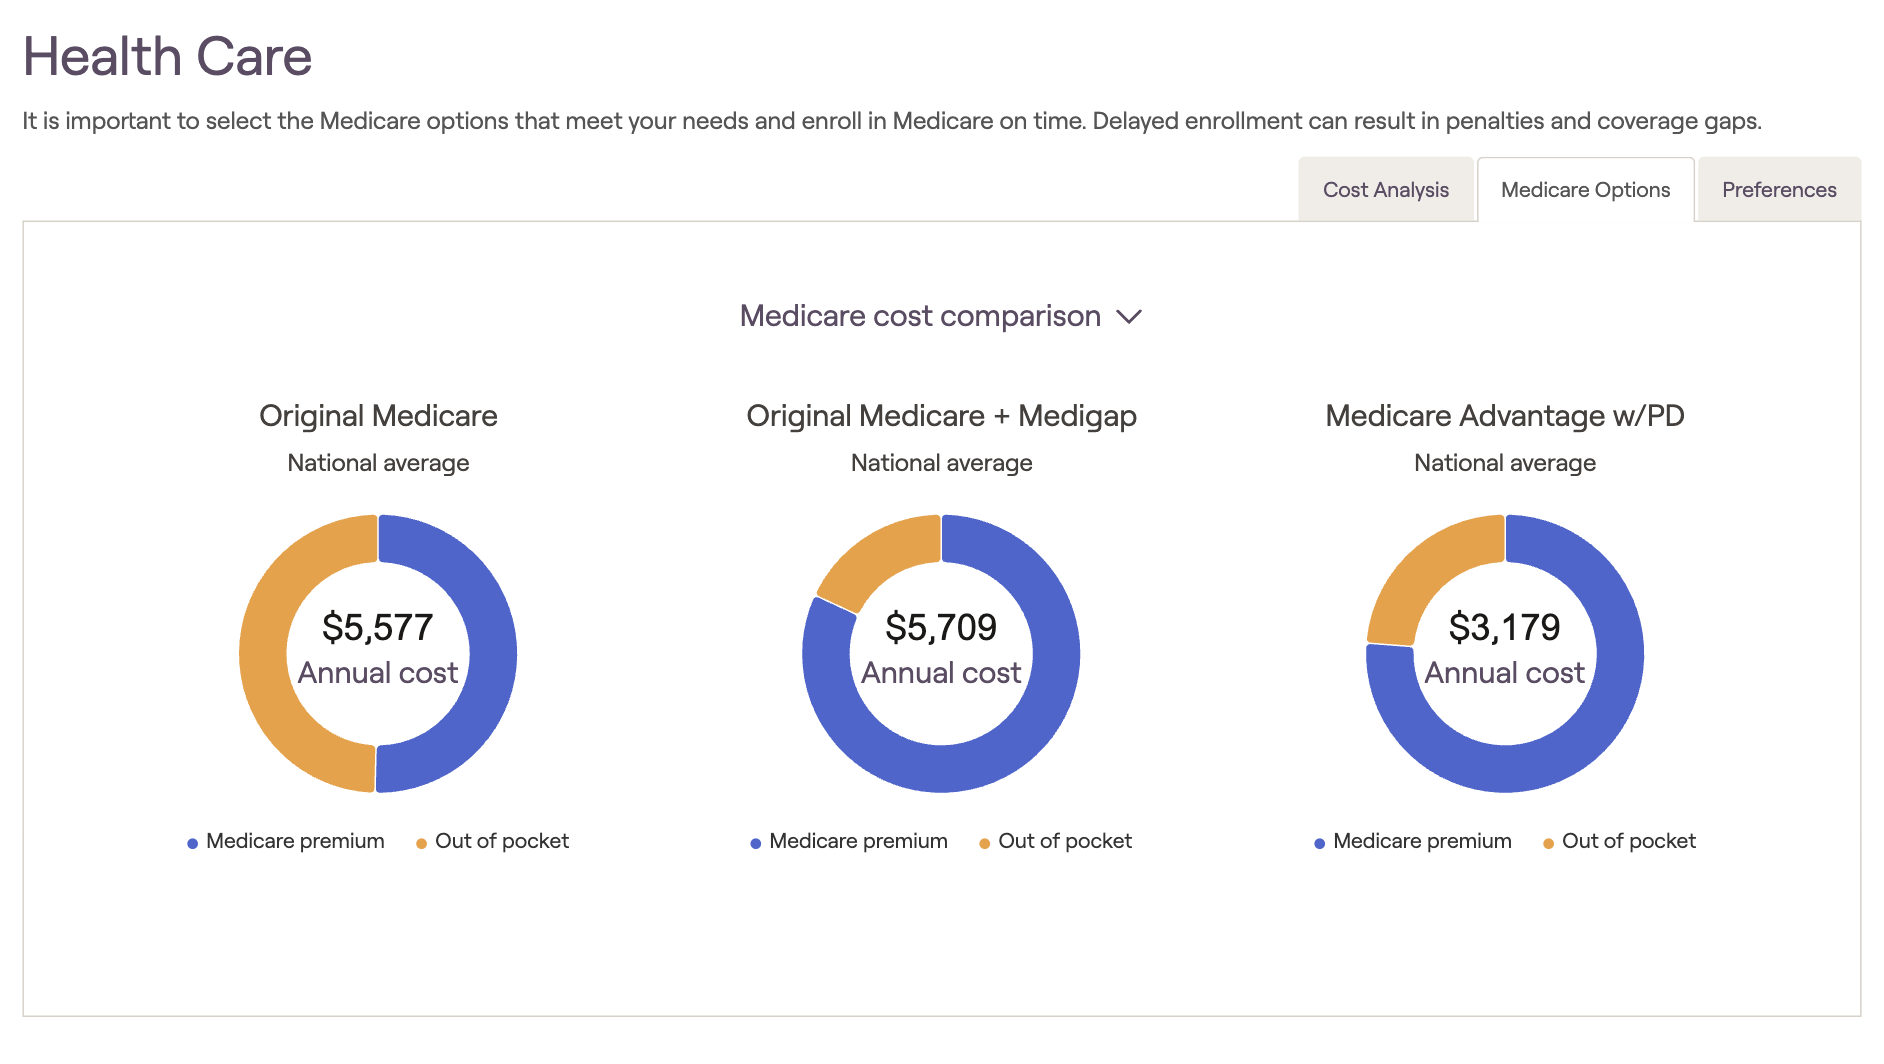
- Medicare option summary: the client's preferences and how it compares to their selected coverage, and their current health care cost
- Consideration and coverage comparisons: side-by-side views of Original Medicare, Original Medicare + Medigap, and Medicare Advantage with prescription drugs
- Cost comparison: projected annual health care costs for each of the three options
- Enrollment period: their Initial Enrollment Period based off of the selections in the preferences tab, with resources & options available to the individual as part of that Initial Enrollment Period
- Medicare tips: extra pointers on Medicare coverage and enrollment
“Cost Analysis” tab
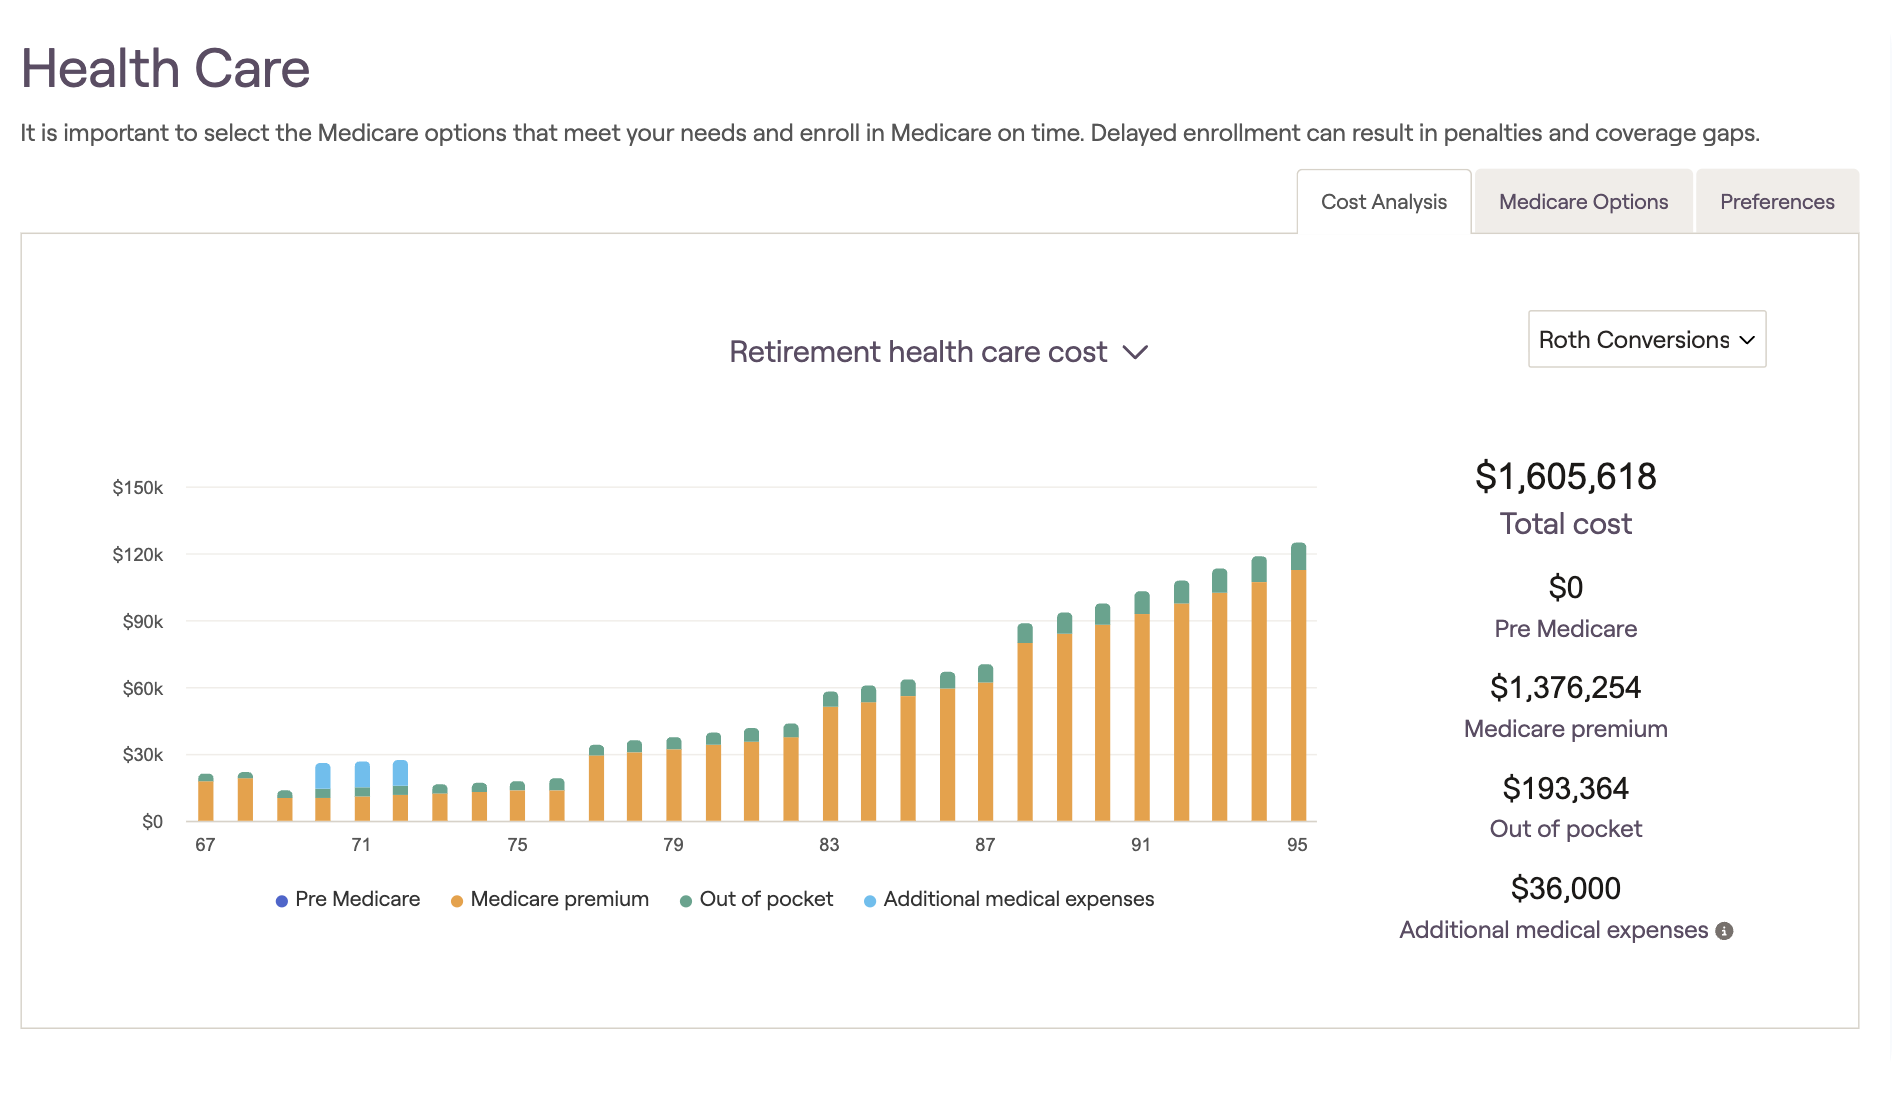
Build realistic health care costs into the plan
Health care projections in RightCapital start with the Annual Retirement Health Cost card in Profile > Goals. You can choose from five cost estimate methods:
- Customized amount: your own annual figure
- National average: based on Milliman data and updated every year
- Original Medicare: a detailed breakdown of pre-Medicare costs, Part B and Part D premiums, and out-of-pocket costs (customized amounts, state averages, and national averages can be used)
- Medicare + Medigap: adds a supplemental Medigap premium
- Medicare Advantage with prescription drugs: national average, state average, or customized amounts
With the Original Medicare option, RightCapital calculates Part B and Part D IRMAA from the plan's projected AGI two years earlier. For clients already on Medicare, you can enter their actual MAGI from the past two years under Gear icon > Settings > Tax Assumptions for a more precise IRMAA calculation.
Retirement health care costs grow at the plan's health care cost inflation rate, and you can see the full breakdown in Retirement > Cash Flows under Summary > Expenses > Health Care.
The move from working life to retirement is a big transition, and getting health care coverage right is often near the top of a client's list. Even after a client has enrolled, Medicare planning continues. Part B and Part D premiums change with income, so the tax strategies you recommend today will show up in their Medicare costs down the road.
RightCapital makes Medicare planning easier by helping advisors answer clients' questions about Medicare plans, guide them through enrollment, and show them how health care fits into their overall financial plan.
Medicare FAQs
The Initial Enrollment Period starts three months before the month a client turns 65 and lasts seven months. Clients whose Social Security benefits begin four or more months before 65 are enrolled in Parts A and B automatically. Clients still working with employer group coverage may be able to delay Part B and use an eight-month Special Enrollment Period later.
Medicare Open Enrollment runs from October 15 to December 7 each year. During this period, beneficiaries can switch between Original Medicare and Medicare Advantage, change Medicare Advantage plans, or join, drop, or switch Part D drug plans. Changes take effect January 1 of the following year.
IRMAA (income-related monthly adjustment amount) is an extra charge added to Part B and Part D premiums when MAGI (modified adjusted gross income) from two years earlier goes above certain thresholds. In 2026, those thresholds are $109,000 for individual filers and $218,000 for joint filers. Roth conversions and other income-raising moves can trigger IRMAA, so advisors should model the effect on Medicare costs alongside the tax savings.
Fidelity Investments' 2026 estimate puts average lifetime health care costs for one person retiring at 65 this year at $185,500, not including long-term care. Part B and Part D premiums account for 45% of that amount.
Yes. RightIntel, included with RightCapital Premium and Platinum subscriptions, shows each client's Medicare filing age, including the month and year, in its Key Events table. It can also send key event notifications when clients reach Medicare filing age.